
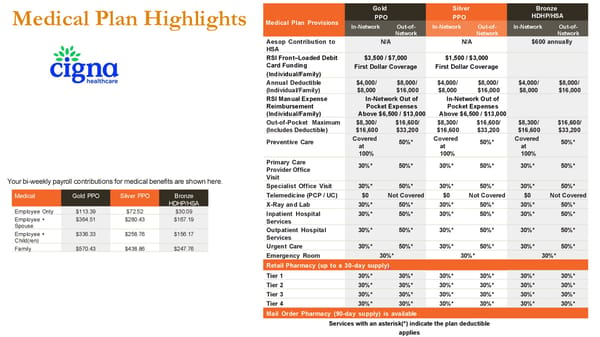
Medical Plan Highlights Medical Plan Provisions Gold PPO Silver PPO Bronze HDHP/HSA In-Network Out-of- Network In-Network Out-of- Network In-Network Out-of- Network Aesop Contribution to HSA N/A N/A $600 annually RSI Front–Loaded Debit Card Funding (Individual/Family) $3,500 / $7,000 First Dollar Coverage $1,500 / $3,000 First Dollar Coverage Annual Deductible (Individual/Family) $4,000/ $8,000 $8,000/ $16,000 $4,000/ $8,000 $8,000/ $16,000 $4,000/ $8,000 $8,000/ $16,000 RSI Manual Expense Reimbursement (Individual/Family) In-Network Out of Pocket Expenses Above $6,500 / $13,000 In-Network Out of Pocket Expenses Above $6,500 / $13,000 Out-of-Pocket Maximum (Includes Deductible) $8,300/ $16,600 $16,600/ $33,200 $8,300/ $16,600 $16,600/ $33,200 $8,300/ $16,600 $16,600/ $33,200 Preventive Care Covered at 100% 50%* Covered at 100% 50%* Covered at 100% 50%* Primary Care Provider Office Visit 30%* 50%* 30%* 50%* 30%* 50%* Specialist Office Visit 30%* 50%* 30%* 50%* 30%* 50%* Telemedicine (PCP / UC) $0 Not Covered $0 Not Covered $0 Not Covered X-Ray and Lab 30%* 50%* 30%* 50%* 30%* 50%* Inpatient Hospital Services 30%* 50%* 30%* 50%* 30%* 50%* Outpatient Hospital Services 30%* 50%* 30%* 50%* 30%* 50%* Urgent Care 30%* 50%* 30%* 50%* 30%* 50%* Emergency Room 30%* 30%* 30%* Retail Pharmacy (up to a 30-day supply) Tier 1 30%* 30%* 30%* 30%* 30%* 30%* Tier 2 30%* 30%* 30%* 30%* 30%* 30%* Tier 3 30%* 30%* 30%* 30%* 30%* 30%* Tier 4 30%* 30%* 30%* 30%* 30%* 30%* Mail Order Pharmacy (90-day supply) is available Medical Gold PPO Silver PPO Bronze HDHP/HSA Employee Only $113.39 $72.52 $30.09 Employee + Spouse $364.51 $280.43 $167.19 Employee + Child(ren) $336.33 $258.76 $156.17 Family $570.43 $438.86 $247.76 Your bi-weekly payroll contributions for medical benefits are shown here. Services with an asterisk(*) indicate the plan deductible applies
 AESOP 2026 Open Enrollment Guide Page 6 Page 8