
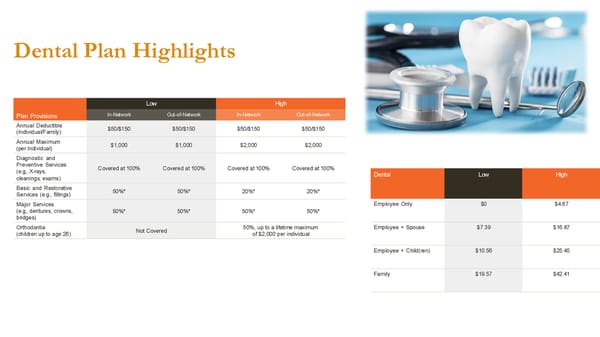
Dental Plan Highlights Dental Low High Employee Only $0 $4.67 Employee + Spouse $7.39 $16.87 Employee + Child(ren) $10.56 $25.45 Family $19.57 $42.41 Plan Provisions Low High In-Network Out-of-Network In-Network Out-of-Network Annual Deductible (Individual/Family) $50/$150 $50/$150 $50/$150 $50/$150 Annual Maximum (per Individual) $1,000 $1,000 $2,000 $2,000 Diagnostic and Preventive Services (e.g., X-rays, cleanings, exams) Covered at 100% Covered at 100% Covered at 100% Covered at 100% Basic and Restorative Services (e.g., fillings) 50%* 50%* 20%* 20%* Major Services (e.g., dentures, crowns, bridges) 50%* 50%* 50%* 50%* Orthodontia (children up to age 26) Not Covered 50%, up to a lifetime maximum of $2,000 per individual
 AESOP 2026 Open Enrollment Guide Page 13 Page 15